
NHS activity and performance summary: August and September 2026
Report summarising data on activity and performance in the Welsh NHS for August and September 2026.
In this page
Introduction
A monthly summary of NHS Wales activity and performance. Long term trends are explored in our annual reports, Trends in NHS urgent and emergency care activity and Trends in NHS planned care activity.
Data are provided by Digital Health and Care Wales (DHCW) and Welsh Ambulance Services University NHS Trust (WAST). Data for each topic area are also available in more detail on StatsWales.
Many of the statistics presented here are based on targets and performance standards established by the previous government. We will continue to report on this basis until those targets and standards are replaced or revised.
Analysis of trends at health board level is provided in a separate data dashboard which is published alongside this report.
Main points
Emergency services (September)
In September there were 759 purple calls to the ambulance service, around 2.2% of all calls, and 4,722 red calls, around 13.4% of all calls.
For patients in cardiac arrest for whom resuscitation was attempted, 25.7% had a return of spontaneous circulation (ROSC) at the time of arrival to hospital, an increase compared with the previous month.
The median response time for purple calls was 7 minutes 31 seconds, longer than the previous month. The median response times for red calls was 9 minutes 32 seconds, longer than the previous month. The target for median response to both purple and red calls is 6 to 8 minutes, meaning the target for purple calls was met and the target for red calls was not.
In September there were just over 98,700 attendances to all emergency departments, an average of 3,291 attendances per day; this was 141 more attendances per day on average than in the previous month and the second highest figure on record.
Performance against the four-hour target improved slightly but performance worsened against the twelve-hour target when compared with the previous month.
The average time spent in emergency departments was slightly shorter than the previous month at 2 hours and 57 minutes.
Treatment waiting lists (August)
There were just over 714,200 referral to treatment (RTT) patient pathways waiting to start treatment, an increase of around 4,500 since July. This is the fifth consecutive monthly increase. The number of patient pathways is not the same as the number of individual patients, because some people have multiple open pathways. More information is available in the 'Chief statistician’s update: explaining NHS activity and performance statistics'.
Management information suggests there were about 558,100 individual patients on treatment waiting lists.
The proportion of pathways waiting less than 26 weeks decreased to 64.2% in August. The number of pathways waiting longer than 36 weeks increased to just under 179,500.
Just under 5,100 pathways were waiting more than two years, 92.8% lower than the peak and an increase of 337 (7.1%) from the previous month.
The average time patients had been waiting for treatment at the end of August was 0.9 weeks longer than the previous month at 17.2 weeks.
Provisional data for September indicate an increase in total pathways waiting but a decrease in pathways waiting more than 2 years.
There were just over 13,100 pathways waiting longer than one year for their first outpatient appointment, an increase from the previous month, but 87.2% less than the peak in August 2022.
Diagnostics and therapies (August)
Diagnostics patient pathways waiting decreased to just over 111,600 in August, the lowest figure since September 2024. The number waiting longer than 8 weeks (the target maximum wait) increased to just over 38,200.
For therapies, pathways waiting decreased to just over 65,600, the second highest figure on record, and the number waiting longer than 14 weeks (the target maximum wait) increased to just under 8,100.
Cancer services (August)
2,000 people started their first definitive treatment in August, 248 fewer than the previous month. The number of patients informed they did not have cancer decreased to 13,574. Performance against the 62 day target worsened in August, falling to 59.9%.
Comparability with UK nations
The 4 nations of the UK publish their own health service statistics. Links to equivalent publications for Scotland, England and Northern Ireland, covering topics similar to those presented in this report for Wales, are provided in the UK nations statistical publications section below.
It is important to note that statistics published by the UK nations are often not directly comparable. This reflects the devolved nature of health services in Wales, Scotland and Northern Ireland, where services are organised and managed differently and are frequently based on distinct concepts, definitions and performance measures. We have worked with the Office for National Statistics (ONS) and statistical leads across the UK to assess where Wales’ official statistics can and cannot be compared with those produced elsewhere.
This work has concluded that Wales’ official ambulance service and cancer performance statistics are not comparable with measures published by the other UK nations. Statistics relating to major emergency departments in Wales are broadly comparable with those for England and Scotland up to September 2026, but not thereafter. For RTT waiting lists, Wales’ statistics are not comparable with those published by Scotland or Northern Ireland. However, a measure broadly comparable with England can be produced by adjusting for differences in the patient pathways included in the published figures. This comparison is presented in the relevant section of this report. Further information on the coherence and comparability of the statistics produced across the 4 UK nations is available in the following articles:
Ambulance calls
Until July 2025, 999 ambulance calls were categorised as red (immediately life-threatening), amber (serious but not life-threatening) or green (non-urgent).
On 1 July a new response model was implemented, and 2 new response categories were introduced to replace the previous red category. The new categories are:
- purple: Arrest, for cardiac and respiratory arrests
- red: Emergency, for major trauma and other incidents where patients are at significant risk of cardiac or respiratory arrest if they do not receive a rapid response
On 2 December 2025, 3 new categories replaced the previous amber and green categories. These are:
- orange: Now, for serious conditions
- yellow: Soon, for people who need to be assessed first
- green: Planned, for less urgent calls
Data up to June 2025 based on the previous response model will remain available on StatsWales, however they are not comparable with the new measures. A wider range of quality indicators are published by the NHS Wales Joint Commissioning Committee. The 'Chief Statistician’s update: explaining NHS activity and performance statistics' provides more information on the background to the new ambulance performance measures.
Activity
Figure 1: number of purple and red emergency ambulance calls, by month [Note 1]
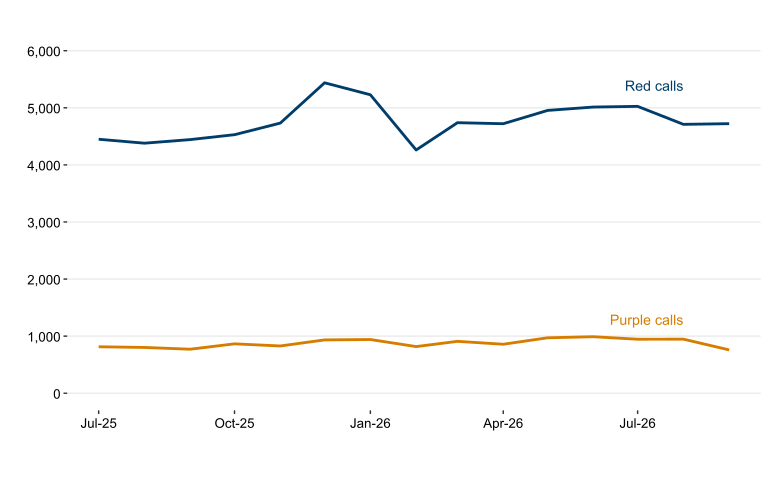
Description of figure 1: a line chart showing the number of purple calls is relatively stable but red calls have been more changeable over time.
Source: Welsh Ambulance Services University NHS Trust
[Note 1]: Detailed definitions for the measures are provided in the accompanying quality report.
Ambulance activity and performance measures, on StatsWales
In September, 759 purple calls were received by the ambulance service (around 2.2% of all calls), a decrease compared with August. 4,722 red calls were received (around 13.4% of all calls), an increase compared with August.
There were:
- 11,868 orange calls
- 5,492 yellow calls
- 1,414 green calls
Performance
Figure 2: return of spontaneous circulation (ROSC) rate, by month [Note 1]
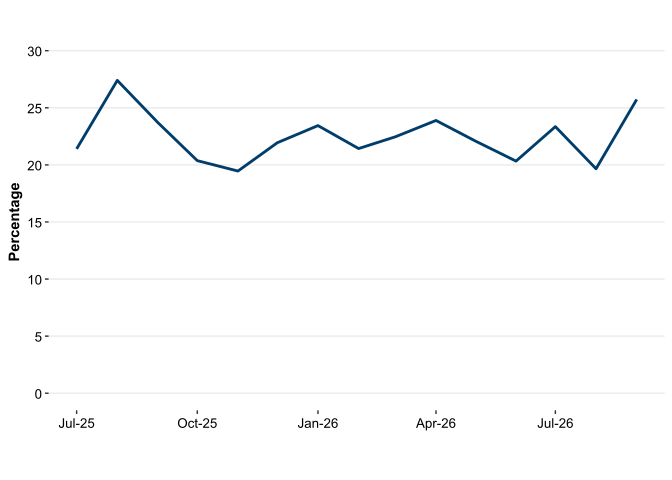
Description of figure 2: a line chart showing return of spontaneous circulation rates has generally fluctuated between 20% and 30%.
Source: Welsh Ambulance Services University NHS Trust
[Note 1]: Detailed definitions for the measures are provided in the accompanying quality report.
Ambulance activity and performance measures, on StatsWales
For patients in cardiac arrest for whom resuscitation was attempted, 25.7% had a return of spontaneous circulation (ROSC) at the time of arrival to hospital, an increase compared with the previous month.
Targets
- For purple and red calls the median and 90th percentile response time targets are 6 to 8 minutes and under 20 minutes respectively.
Figure 3: median and 90th percentile response times for purple and red emergency ambulance calls (minutes and seconds), by month [Note 1]
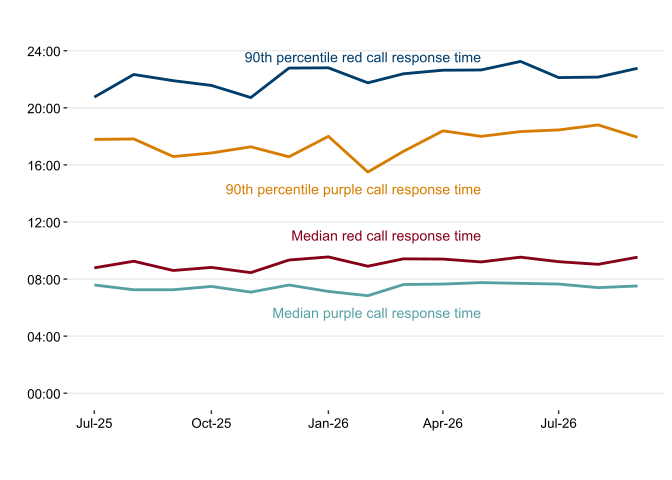
Description of figure 3: a line chart showing median and 90th percentile response times are shorter for purple calls than red calls, and all are relatively stable recently.
Source: Welsh Ambulance Services University NHS Trust
[Note 1]: Detailed definitions for the measures are provided in the accompanying quality report.
Ambulance activity and performance measures, on StatsWales
The median response time for purple calls was 7 minutes 31 seconds, slightly longer than in August. The 90th percentile (the point at which 90% of responses were quicker and 10% were slower) was 17 minutes 56 seconds, shorter than in August. The response time targets for purple calls were both met.
For red calls, the median increased to 9 minutes 32 seconds and the 90th percentile increased to 22 minutes 46 seconds. This means the response time targets for red calls were not met.
Figure 4: median response time for orange ambulance calls (hours, minutes and seconds), by month
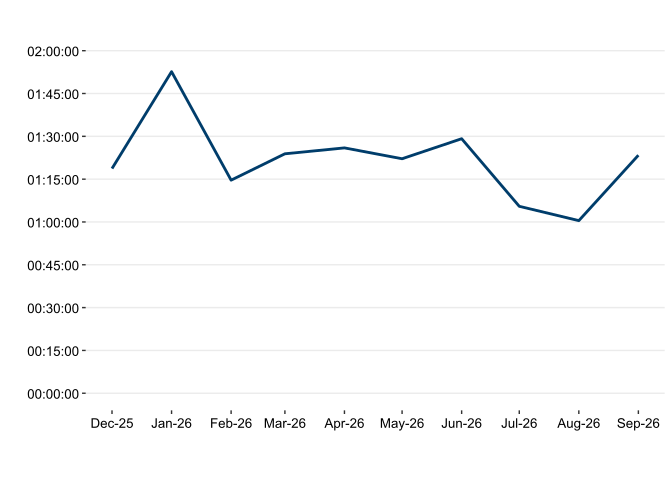
Description of figure 4: a line chart showing the median response time for orange calls was 1 hour and 53 minutes in January, but has been under 1 hour and 30 minutes since.
Source: Welsh Ambulance Services University NHS Trust
Ambulance activity and performance measures, on StatsWales
Figure 5: median time for Public Access Defibrillator (PAD) arrival, to commence CPR instruction, and to identify cardiac arrest (minutes and seconds), by month [Note 1]
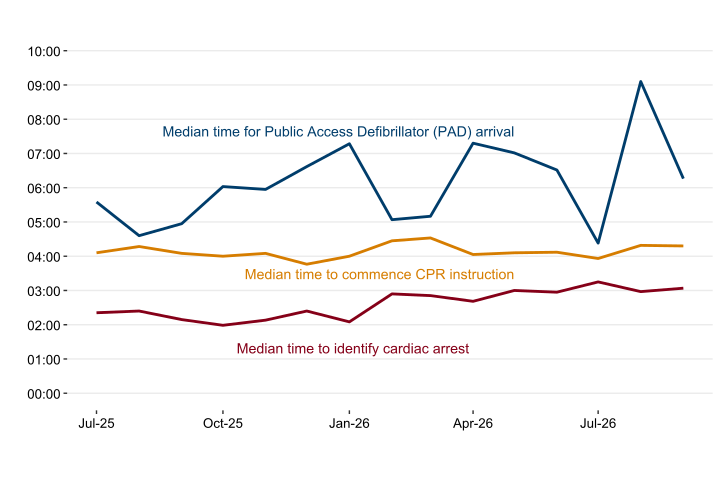
Description of figure 5: a line chart showing the median time for PAD arrival has fluctuated, while the median times to commence CPR instruction and to identify cardiac arrest have been more stable.
Source: Welsh Ambulance Services University NHS Trust
[Note 1]: Detailed definitions for the measures are provided in the accompanying quality report.
Ambulance activity and performance measures, on StatsWales
The median time for the arrival of a PAD was 6 minutes and 16 seconds. The median time to commence CPR instruction was 4 minutes and 18 seconds, and the median time to identify cardiac arrest was 3 minutes and 4 seconds.
Ambulance handovers
Performance
Patient handover times between ambulance crews and hospital staff are monitored because they affect the experience of ambulance patients themselves, as well as the ambulance service's ability to respond promptly to other emergency calls.
Targets
- People arriving at hospital by ambulance should be handed over to hospital staff within 15 minutes, in line with clinical priority. Where this is not achievable, handovers should not exceed 45 minutes.
Figure 6: percentage of ambulance handovers completed within 15 minutes and 45 minutes, by month [Note 1]
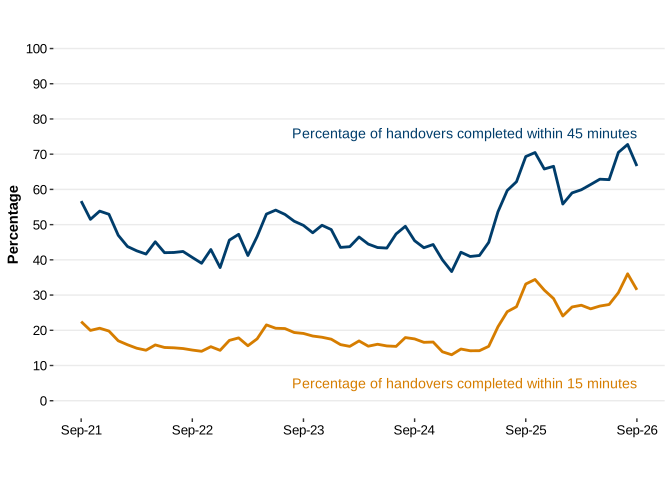
Description of figure 6: a line chart showing the percentages of ambulance handovers completed within 15 minutes and 45 minutes have increased recently.
Source: Welsh Ambulance Services University NHS Trust
Ambulance handovers, on StatsWales
[Note 1]: Data on the percentage of handovers within 15 minutes are also published in the Joint Commissioning Committee’s Ambulance Service Indicators (ASIs). The figures differ from those presented here because the ASIs include some different hospitals, wards and vehicles. The ASIs are designed to reflect patient experience, whereas the statistics in this report are intended to reflect the performance of local health boards. Further details are available in the accompanying StatsWales dataset.
Emergency departments
Activity
Figure 7: average attendances in emergency departments, and admissions to hospital resulting from attendances at major emergency departments per day, by month [Note 1]
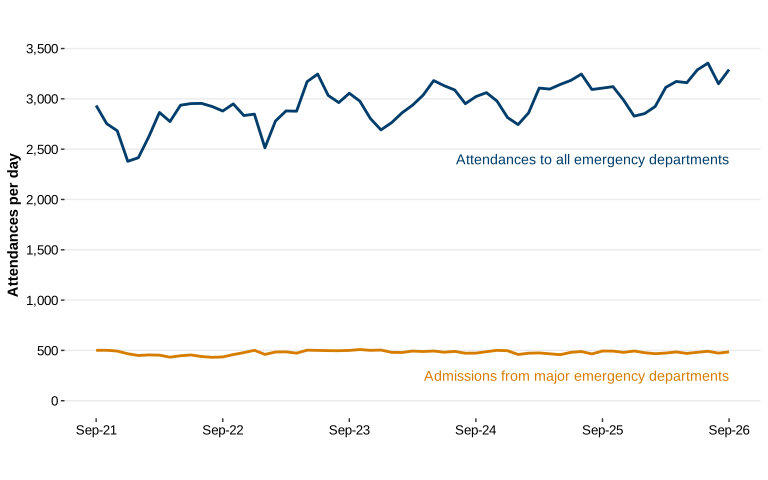
Description of figure 7: a line chart showing no discernible trend in attendances to emergency departments.
Source: Emergency department data set, DHCW
Emergency departments: attendances by age and sex, April 2016 onwards, on StatsWales
[Note 1]: Chart shows number of attendances at both major emergency departments and minor injuries units, and the number of admissions resulting from attending major emergency departments only.
In September there were just over 98,700 attendances to all emergency departments, an average of 3,291 attendances per day; this was 141 more attendances per day on average than in the previous month and the second highest figure on record.
Just under 14,600 patients were admitted to hospital following attendance at major emergency departments. This was 0.6% lower than the previous month.
Performance
Targets
- 95% of new patients should spend less than 4 hours in emergency departments from arrival until admission, transfer or discharge.
- No patient waiting more than 12 hours in emergency departments from arrival until admission, transfer or discharge.
Figure 8: percentage of patients admitted, transferred or discharged within 4 hours at emergency departments, by month
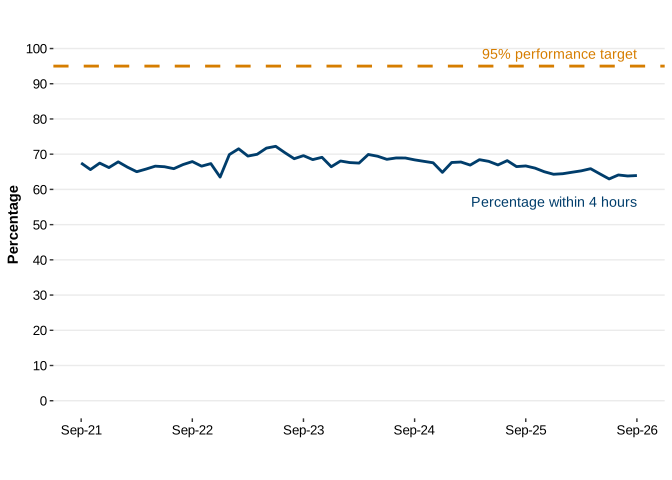
Description of figure 8: a line chart showing the percentage of patients admitted, transferred or discharged within 4 hours at emergency departments has been relatively stable in recent years, between 60 and 70%.
Source: Emergency department data set, DHCW
In September, 63.9% of patients spent less than 4 hours in emergency departments from arrival until admission, transfer or discharge. This was slightly higher than the previous month.
The median waiting time was 2 hours and 57 minutes, down 1 minute from the previous month. Waiting times vary by age, time of day and day of the week, with further detail available in the Trends in NHS urgent and emergency care activity report.
From 1 October 2026, guidance on clinical exceptions was removed. Previously, this allowed the clock to stop when treatment ended for certain patients, rather than when they physically left the department. As a result, figures from October 2026 onwards will not be directly comparable with earlier data. We estimate this change will reduce the 4-hour performance measure by around 3 to 5 percentage points. Further information on the impact on official statistics and comparability with other UK nations will be provided in due course.
Figure 9: patients waiting more than 12 hours to be admitted, transferred or discharged at NHS emergency departments, by month
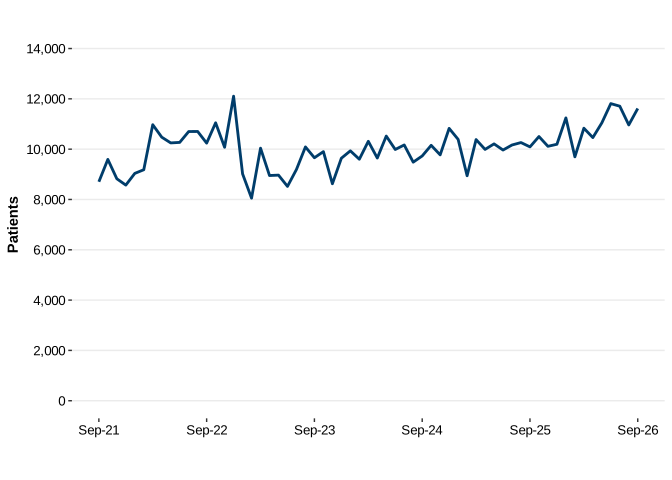
Description of figure 9: a line chart showing the number of patients waiting longer than 12 hours to be admitted, transferred or discharged at emergency departments has increased gradually in the past few years.
Source: Emergency department data set, DHCW
In September, 11,616 patients waited 12 hours or more. This was 653 (6.0%) higher than in the previous month.
Outpatient appointments
Activity
Figure 10: average daily referrals for first outpatient appointment, by month
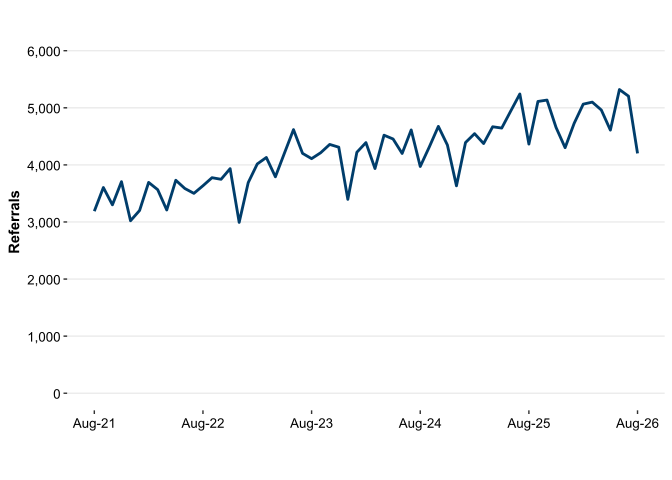
Description of figure 10: a line chart showing outpatient referrals, which has been fluctuating with an upwards trend.
Source: Outpatient Referral Dataset, DHCW
Outpatient referrals, April 2012 onwards, on StatsWales
An average of 4,201 referrals for first outpatient appointments were made per day in August. This is a decrease of 19.3% (1003 fewer referrals per day on average) compared to July.
Performance
Targets
- No one waiting for longer than a year for their first outpatient appointment by the end of 2022 (a target established in the planned care recovery plan).
Figure 11: pathways waiting more than a year for their first appointment, by month
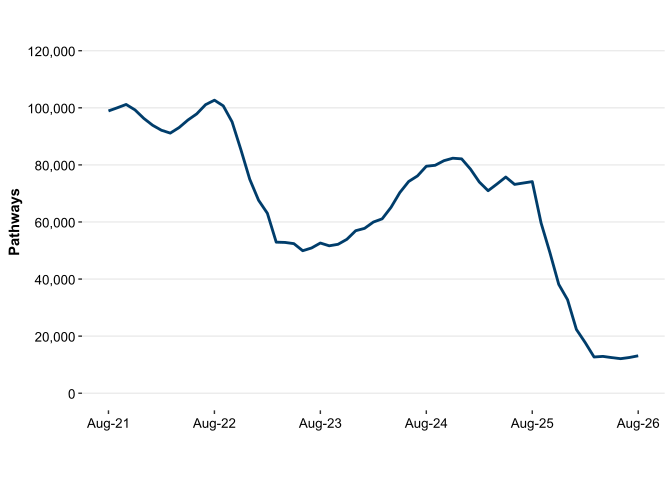
Description of figure 11: a line chart showing the number of patient pathways waiting longer than a year has fallen considerably recently.
Source: Referral to treatment times, DHCW
In August, the number of pathways waiting longer than one year for their first outpatient appointment increased by 4.8% compared to the previous month to just over 13,100. This was 87.2% lower than the peak in August 2022.
Diagnostics and therapies
Activity
Figure 12: patient pathways waiting for diagnostic and therapy services, by month [Note 1] [Note 2]
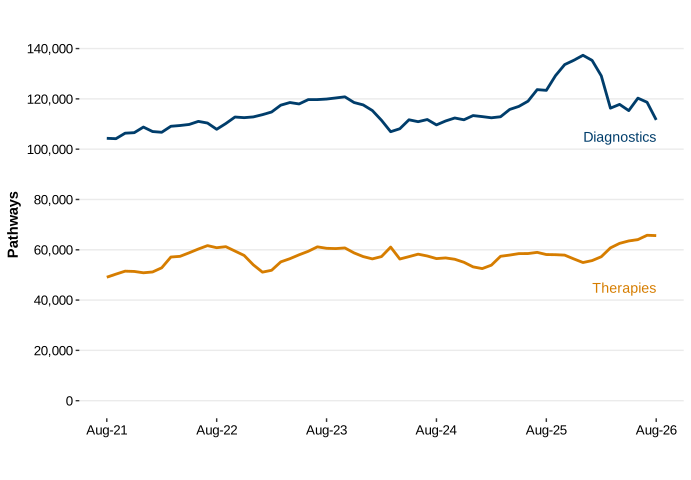
Description of figure 12: a line chart showing a recent fall in pathways waiting for diagnostics, and a recent increase for therapy services.
Source: Diagnostic and therapy services waiting times, DHCW
Therapy services: pathway waiting times, grouped weeks waiting, October 2009 onwards, on StatsWales
[Note 1]: From April 2024 audiology and weight management pathways were no longer reported in the therapies data.
[Note 2]: There are known issues affecting the quality and consistency of the published diagnostics statistics, particularly for radiology pathways. Work is ongoing to understand the extent of the issues and the impact on the published figures. Users should therefore exercise caution when comparing health boards, as previously published data may be subject to revision.
In August there were just over 111,600 patient pathways waiting for diagnostics, a decrease of 5.9% compared with the previous month and the lowest figure since September 2024.
In August there were just over 65,600 patient pathways waiting for therapies, a decrease of 0.2% compared with the previous month and the second highest figure on record.
Performance
Targets
- The maximum wait for access to specified diagnostic tests is 8 weeks.
- The maximum wait for access to specified therapy services is 14 weeks.
- The planned care recovery plan established a target date of Spring 2024 to reach these targets.
Figure 13: patient pathways waiting over the target time for diagnostic and therapy services, by month [Note 1] [Note 2]
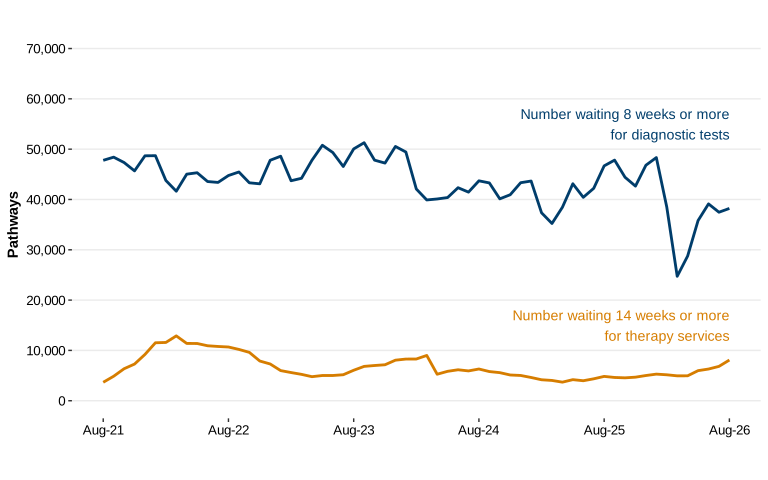
Description of figure 13: a line chart showing a fluctuating trend in diagnostics pathways waiting longer than 8 weeks and a stable trend in therapies pathways waiting longer than 14 weeks.
Source: Diagnostic and therapy services waiting times, DHCW
Therapy services: pathway waiting times, grouped weeks waiting, October 2009 onwards, on StatsWales
[Note 1]: From April 2024 audiology and weight management pathways were no longer reported in the therapies data, meaning they are not directly comparable with data up to March 2024.
[Note 2]: There are known issues affecting the quality and consistency of the published diagnostics statistics, particularly for radiology pathways. Work is ongoing to understand the extent of the issues and the impact on the published figures. Users should therefore exercise caution when comparing health boards, as previously published data may be subject to revision.
In August, just over 38,200 pathways were waiting longer than the target time for diagnostics, an increase of 2.0% compared to July.
There were just under 8,100 therapies pathways waiting longer than the target time, an increase of 18.4% compared to the previous month and the highest figure since March 2024.
The median waiting time for diagnostic tests was 5.1 weeks, 0.2 weeks longer than in July, and for therapy services it was 5.3 weeks, 0.7 weeks longer than in July and the highest figure since December 2023.
Referral to treatment waiting times
Referral to treatment statistics cover open and closed pathways following referral by a GP or other medical practitioner to hospital for treatment. Open pathways are those that remain on the waiting list for treatment, whereas closed pathways are those removed.
Activity is measured by patient pathways, which differs to the number of patients. More information on this difference is available in the Welsh Government’s 'Chief statistician’s update: explaining NHS activity and performance statistics'.
Performance
Targets and objectives
- Eliminate waits longer than 2 years.
- 95% of patients should wait less than 26 weeks from referral.
- No patients should wait more than 36 weeks for treatment from referral.
Figure 14: patient pathways waiting to start treatment, by month [Note 1]
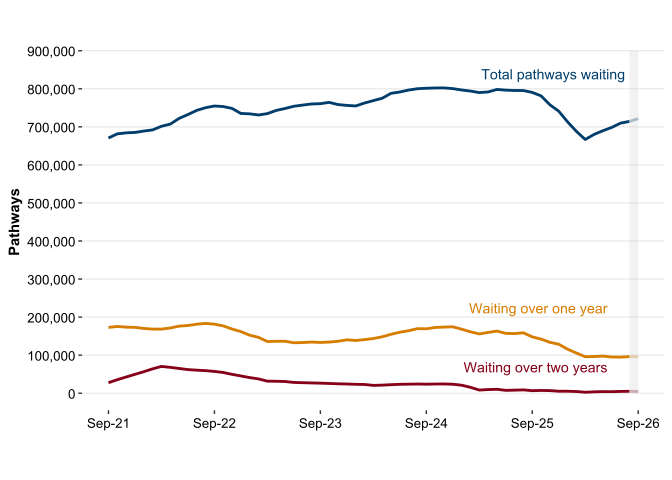
Description of figure 14: a line chart showing that after peaking in late 2024, total pathways started to fall before rising again in recent months. Pathways waiting longer than one year have been stable in recent months and two year waits started falling in early 2022.
Source: Referral to treatment times, DHCW
[Note 1]: Figures in the shaded area for the most recent month in this chart are provisional and are subject to change. The official data series ends in the previous month.
In August there were just over 714,200 patient pathways waiting to start treatment, an increase from July (709,700). Just over 96,200 pathways were waiting more than one year in August, an increase of 1.3% from last month. Just under 5,100 were waiting more than two years, 7.1% higher than last month but 92.8% lower than the peak in March 2022.
These official statistics are published with a lag of around 7 weeks from the end of the reference period. However, given the interest in referral to treatment (RTT) waiting lists and the Welsh Government’s commitment to reducing the longest waits, there is public value in making data on this topic available earlier. We are therefore providing provisional estimates for the month ahead.
Provisional data indicate there were around 721,400 total pathways waiting at the end of September, of which:
- 96,000 were waiting more than 1 year
- 4,900 were waiting more than 2 years
These provisional estimates are subject to change before the official figures for September are released in November.
Headline measures for open pathways across the UK are not comparable. There are large differences in coverage between Wales, Scotland and Northern Ireland statistics, meaning they should not be compared at all. With England, a broadly comparable number can be produced for Wales by removing some known non-consultant led pathways which are not counted in England.
On that basis, there are around 634,000 open pathways on consultant-led pathways in Wales, equivalent to 20 pathways for every 100 people. For England, the figure in August was 13 pathways for every 100 people. These comparisons are explored further in the 'Chief Statistician’s update: comparing NHS performance statistics across the UK'.
The number of patient pathways is not the same as the number of individual patients, because some people have multiple open pathways. Management information suggests there were around 558,100 individual patients on treatment waiting lists in Wales. Estimates for the number of individual patients waiting to start treatment by health board can be found in the NHS waiting lists: estimate of unique patients dataset on StatsWales.
Figure 15: percentage of patient pathways waiting less than 26 weeks, by month
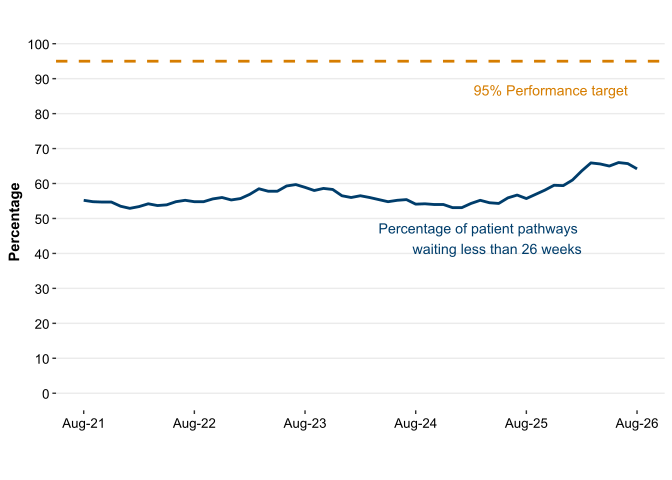
Description of figure 15: a line chart showing the percentage of patient pathways waiting less than 26 weeks has increased recently.
Source: Referral to treatment times, DHCW
Of the just over 714,200 patient pathways waiting to start treatment, by the end of August, 64.2% had been waiting less than 26 weeks. This was lower than the previous month.
Figure 16: patient pathways waiting more than 36 weeks, by month
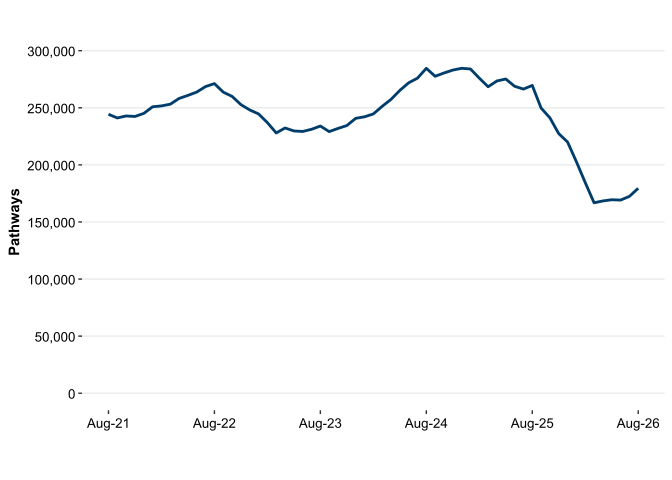
Description of figure 16: a line chart showing the number of pathways waiting more than 36 weeks fell from the end of 2024 but has started to rise recently.
Source: Referral to treatment times, DHCW
In August, just under 179,500 patient pathways had been waiting more than 36 weeks. This was around 7,100 higher than in the previous month. This figure represents 25.1% of all pathways waiting to start treatment.
The median time waiting to start treatment in August was 17.2 weeks, 0.9 weeks longer than the previous month.
Figure 17: closed patient pathways, by month
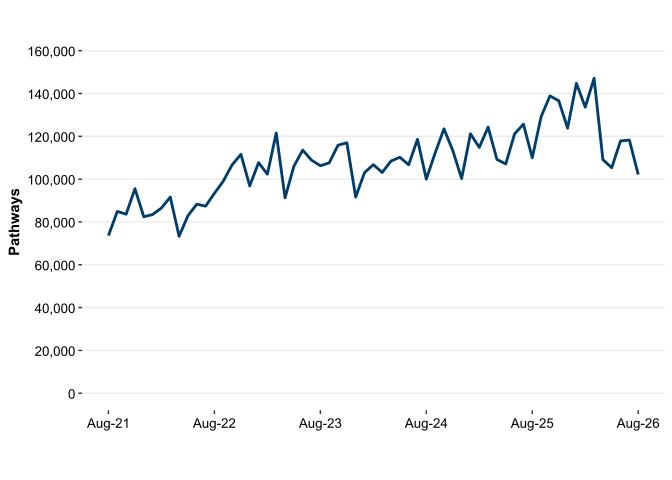
Description of figure 17: a line chart showing the number of patient pathways closed increased in the last few years but has fallen recently.
Source: Referral to treatment times, DHCW
NHS waiting lists: closed referral to treatment pathways, September 2011 onwards (StatsWales)
The number of patient pathways closed in August was just under 102,200. This was an average of 5,109 pathways closed per working day, a decrease of 32 patient pathways closed per working day from the previous month.
Hospital discharge delays
Hospital discharge delays occur when patients who are clinically ready for discharge cannot leave hospital because the necessary ongoing care and support or suitable accommodation is not yet accessible. The figures represent the number of adults who were ready to return home or move on to the next stage of care, that experienced a delay in their transfer of more than 48 hours. The data are a snapshot of delays on a given day each month, meaning they do not tell us the total number of delays over the month. Figures are available for the number of individual delays and the corresponding total number of days delayed experienced by those patients.
Figure 18: number of pathway of care delays and the total days delayed, by month [Note 1]
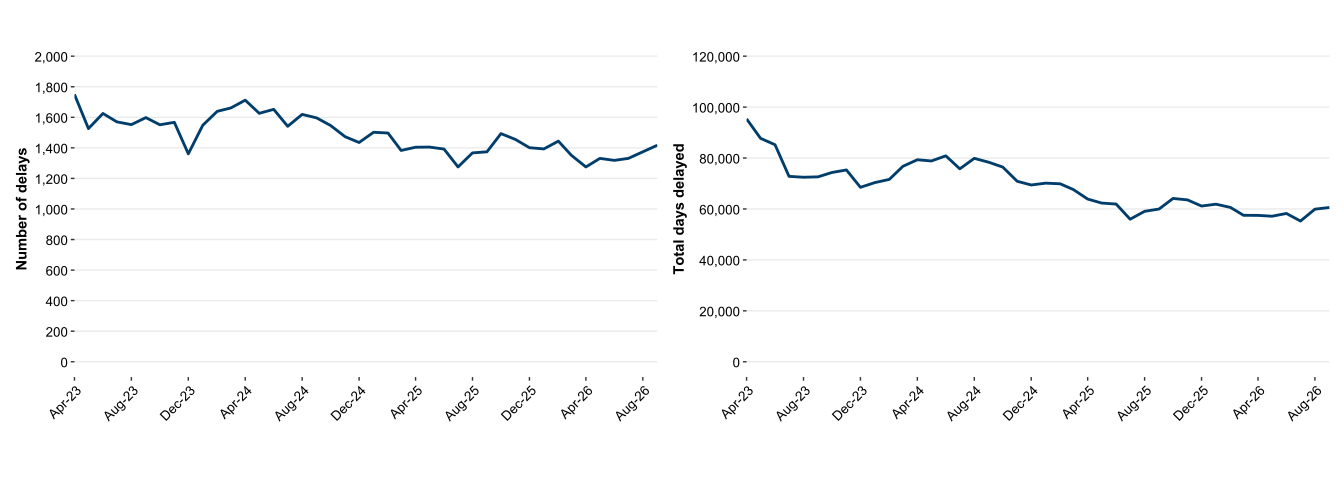
Description of figure 18: line charts showing the number of delays and the total days delayed have fallen in recent years.
Source: Pathway of Care Delays, DHCW
Delayed hospital discharges: total pathway of care delays and total days delayed, on StatsWales
[Note 1] The vertical axes of these charts are on different scales.
In September there were just over 1,400 pathway of care delays on the day the data were collected, an increase compared to the figure in August. The total cumulative days delayed for those patients was just under 60,600, an increase compared to the figure in August.
Cancer services
Activity
Figure 19: closed suspected cancer pathways in the month, by month and outcome
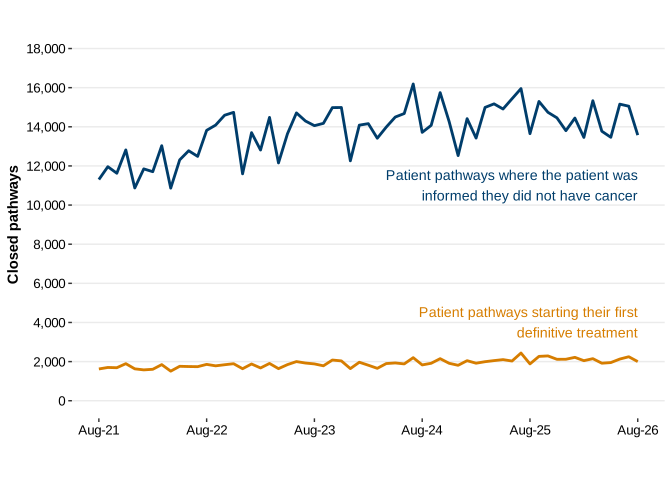
Description of figure 19: a line chart showing the number of patient pathways informed they do not have cancer, which fluctuates, and the number starting their first definitive treatment, which is relatively stable.
Source: Suspected Cancer Pathway, DHCW
In August, 2,000 pathways started cancer treatment, 248 fewer than in July. 13,574 pathways were closed after patients were informed they did not have cancer, a decrease of 9.8%. There were 15,665 new suspected cancer pathways, a decrease of 2764 (15.0%) from July. In recent years the number of new pathways opened has been relatively stable.
Performance
Target
- At least 75% of patients should start treatment within 62 days (without suspensions) of first being suspected of cancer.
Figure 20: percentage of pathways where the patient started their first definitive treatment within the target time, by month
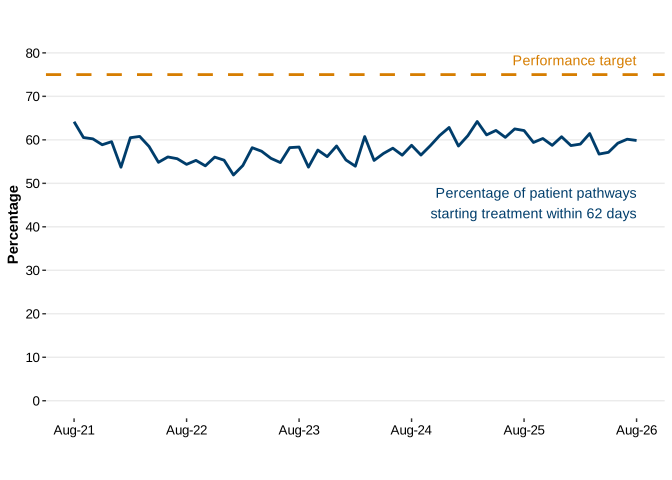
Description of figure 20: a line chart showing the percentage of patients starting treatment within 62 days of a suspicion of cancer has generally fluctuated between 50% and 65% in recent years, with no discernible trend.
Source: Suspected Cancer Pathway, DHCW
In August, 59.9% of pathways started their first definitive treatment within 62 days of first being suspected of cancer. This was a decrease compared with the previous month.
Focus on local health boards
A new monthly dashboard has been developed to replace the quarterly release NHS performance for Welsh local health boards. Summary analyses are provided in this section. These analyses are on a health board provider basis, not health board of residence. This means patients resident in one health board but on waiting lists provided by other health boards are counted in those organisations’ figures. This is consistent with the performance management framework in Wales, in that standards and targets are assessed on a provider basis.
Of the measures covered in this report:
- all health boards except Betsi Cadwaladr and Cardiff and Vale have either no pathways waiting longer than 2 years or less than 1%
- Swansea Bay currently has no one-year waits for a first outpatient appointment, while Cwm Taf Morgannwg has less than 1%
- Swansea Bay has no therapies pathways waiting over 14 weeks
Ambulance service
- A range of new ambulance performance metrics were introduced in July 2025. Health board figures are published on StatsWales. However, it is not possible to summarise these in the format of the main measures for the other topics as below.
Emergency departments
- Swansea Bay has the best 4-hour performance (71.3% attendances under 4 hours) and Betsi Cadwaladr has the worst (57.4%).
- Cardiff and Vale has the best 12-hour performance (8.9% attendances over 12 hours) and Betsi Cadwaladr has the worst (17.5%).
RTT pathways
- Betsi Cadwaladr has the highest proportion of RTT pathways waiting longer than one and 2 years (16.6% and 1.3%).
- Powys has the lowest proportion over one year (2.2%) and Powys and Swansea Bay have no pathways waiting longer than 2 years.
Outpatient appointments
- For first outpatient waits over one year, Cardiff and Vale has the highest proportion at 10.1% of pathways, while Swansea Bay has no pathways waiting.
Diagnostics and therapies
- Cardiff and Vale has the highest proportion of diagnostic breaches over 8 weeks (51.0%) while Powys has the lowest (5.7%).
- For therapies, Hywel Dda has the highest proportion over 14 weeks (31.8%), while Swansea Bay has no pathways waiting over 14 weeks.
Cancer services
- Cwm Taf Morgannwg has the highest proportion of patients starting treatment within 62 days (66.2%), and Swansea Bay has the lowest (41.0%).
More detailed data is available on StatsWales: health and social care.
Figure 21: local health board performance summary, August and September 2026 [Note 1]
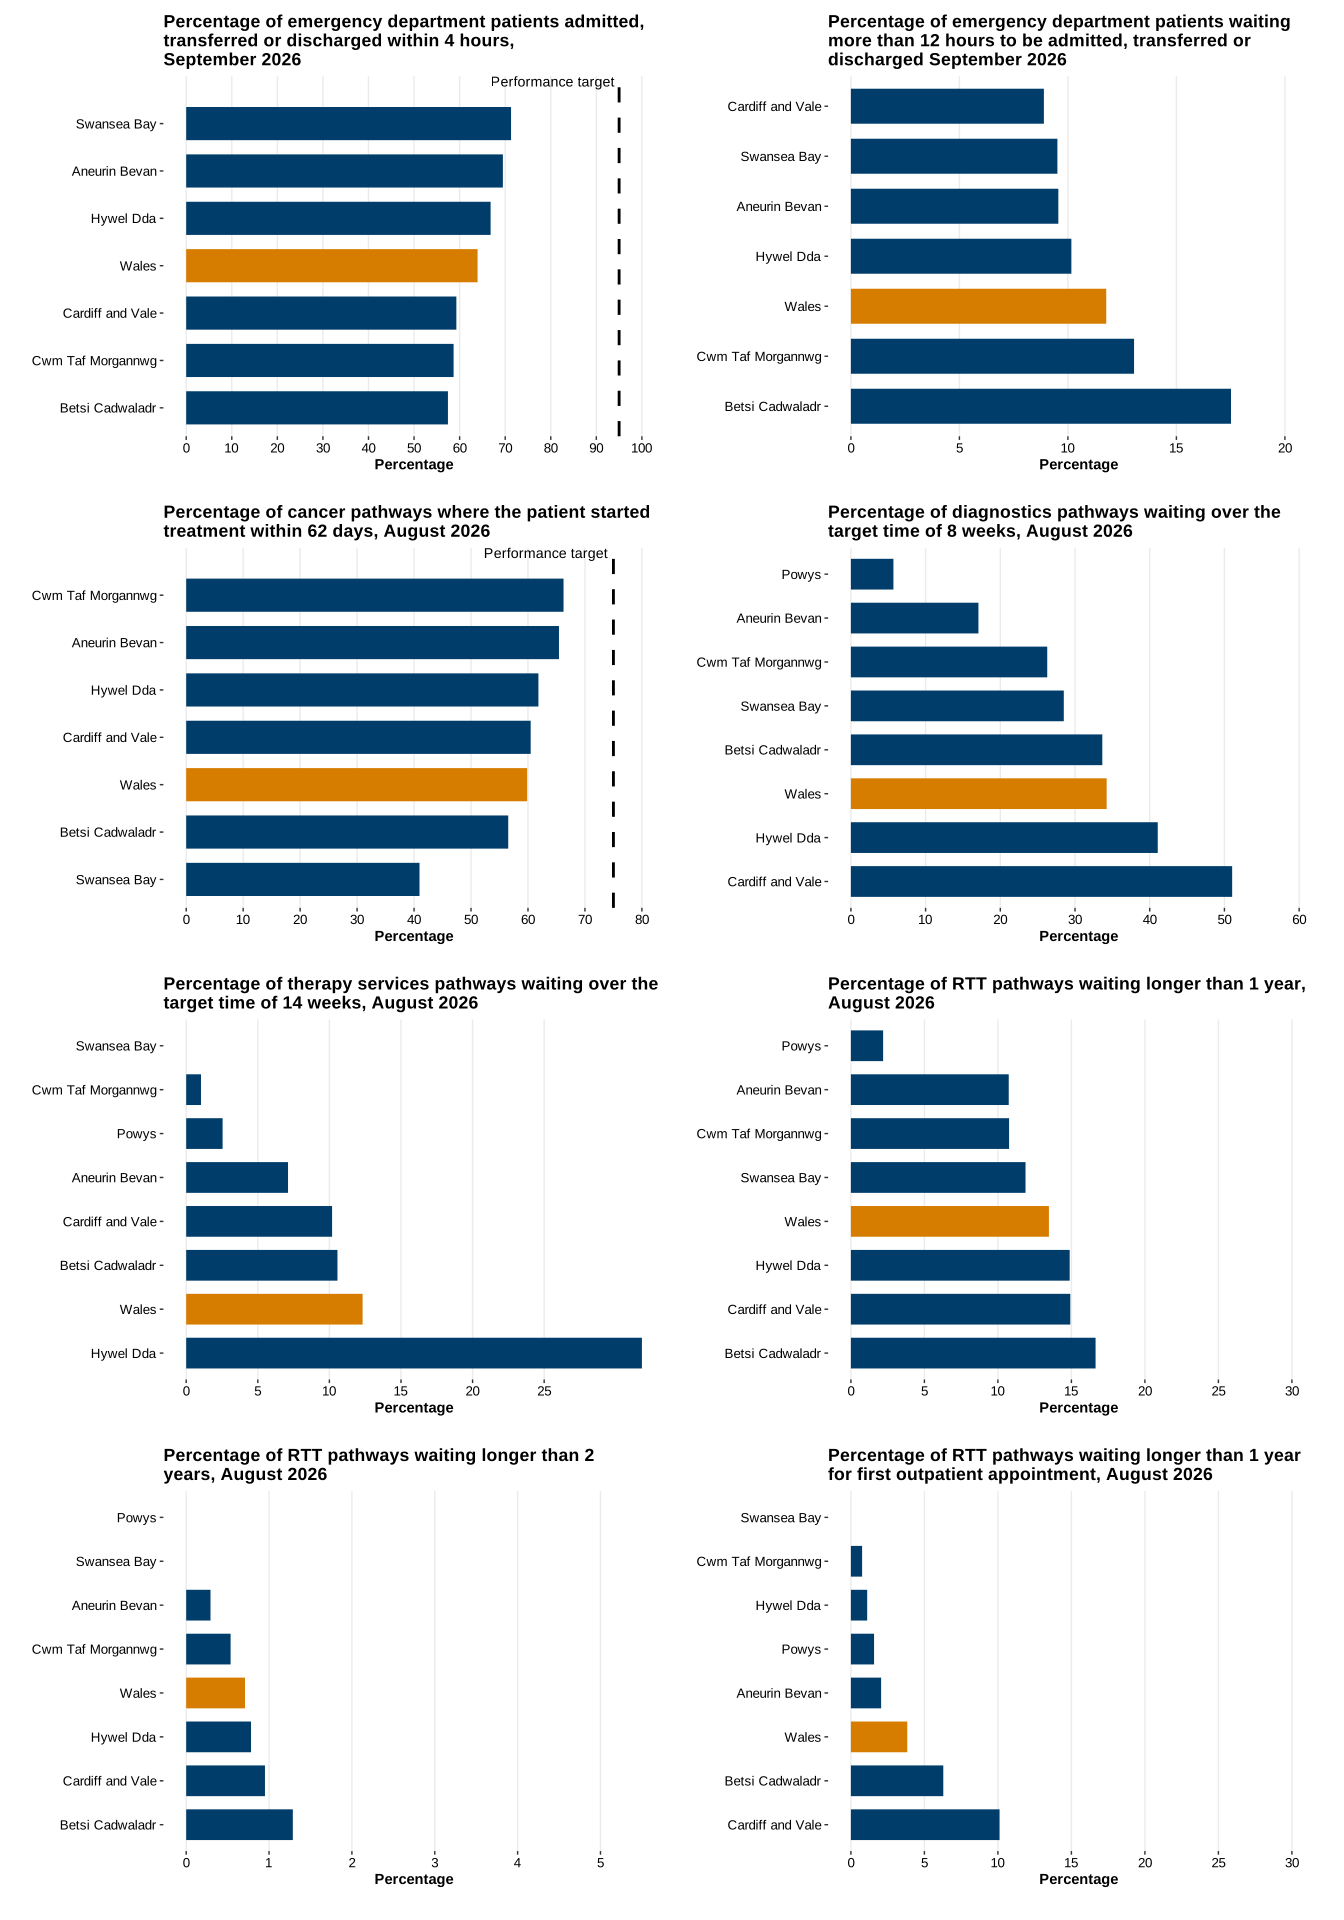
Description of figure 21: a series of charts showing comparative performance for the health boards for selected measures across emergency and planned care in Wales. The main points are summarised in the narrative section above.
Source: Wales Ambulance Services NHS Trust, DHCW
Health and Social Care statistics, on StatsWales
[Note 1]: The percentage axes of these charts are on different scales and care should be taken when looking at the size of differences between health boards.
Quality and methodology information
All quality and methodology information in relation to this statistical release can be found in the NHS activity and performance summary: quality report
Official statistics status
All official statistics should show the standards of the Code of Practice for Statistic (UK Statistics Authority).
These are accredited official statistics. They were independently reviewed by the Office for Statistics Regulation (OSR) in July 2012. They comply with the standards of trustworthiness, quality, and value in the Code of Practice for Statistics.
It is Welsh Government’s responsibility to maintain compliance with the standards expected of accreditation. If we become concerned about whether these statistics are still meeting the appropriate standards, we will discuss any concerns with OSR promptly. Accreditation can be cancelled or suspended at any point when the highest standards are not maintained, and reinstated when standards are restored.
Accredited official statistics (OSR) are called National Statistics in the Statistics and Registration Service Act 2007.
Statement of compliance with the Code of Practice for Statistics
Our statistical practice is regulated by the OSR. OSR sets the standards of trustworthiness, quality and value in the Code of Practice for Statistics that all producers of official statistics should adhere to.
All of our statistics are produced and published in accordance with a number of statements and protocols to enhance trustworthiness, quality and value. These are set out in the Welsh Government’s Statement of Compliance.
These accredited official statistics demonstrate the standards expected around trustworthiness, quality and public value in the following ways.
Trustworthiness
These statistics are compiled from a range of sources derived from administrative data systems in use across the NHS in Wales. Data on the 111 service, 999 ambulance calls and ambulance response times are provided by the Wales Ambulance Services University NHS Trust (WAST), and all other data sources are collected by the Welsh Local Health Boards and provided to Digital Health and Care Wales (DHCW) to enable them to be collated at a national level.
The data collections are overseen by the Welsh Information Standards Board (WISB), which is the custodian of the Information Standards Assurance Process. WISB mandates data collections through the NHS and local heath boards, appraises information standards and provides assurance on matters related to confidentiality and consent.
The published figures are compiled by professional analysts using the latest available data and applying methods using their professional judgement and analytical skillset.
These statistics are pre-announced on the Statistics and Research area of the Welsh Government website. Access to the data during processing is restricted to those involved in the production of the statistics, quality assurance and for operational purposes. Pre-release access is restricted to eligible recipients in line with the Code of Practice (UK Statistics Authority).
Quality
Statistics published by Welsh Government adhere to the Statistical Quality Management Strategy which supplements the Quality pillar of the Code of Practice for Statistics and the European Statistical System principles of quality for statistical outputs.
Data standards and definitions are established by the WISB. Guidance is issued to the data providing organisations and training provided to staff responsible for collecting the data at source. DHCW collates and validates health board level data and queries anomalous and missing data directly with the health boards. Before validated datasets are provided by DHCW to Welsh Government, all data are signed off by health boards. DHCW provides validated datasets to Welsh Government, where analysts process the data to produce the aggregate statistics in the format required for publication. Welsh Government undertakes final validation checks which can be queried with DHCW and the health boards before publication. The statistical release is signed off by senior statisticians before publication.
Value
The purposes of this statistical release and the accompanying data published on StatsWales are to:
- provide evidence for policy development
- inform the media and wider public about activity and performance in the Welsh NHS
- enable service providers such as local health boards and WAST to monitor their own performance
Reliable statistics on the volume of activity undertaken in the NHS, the size of waiting lists, ambulance response times and emergency department and cancer waiting times are vital to inform users about the state of NHS services and the performance of the Welsh government and the local health boards. These services have a significant impact on citizens’ lives and these topics feature prominently in media coverage and political discourse.
The information published here also supports the Welsh Government’s long term plan for health and social care: A healthier Wales.
The timeliness of the data provides the most recent update using reliable data.
You are welcome to contact us directly with any comments about how we meet these standards. Alternatively, you can contact OSR by emailing regulation@statistics.gov.uk or via the OSR website.
Well-being of Future Generations Act (WFG)
The Well-being of Future Generations Act 2015 is about improving the social, economic, environmental and cultural wellbeing of Wales. The Act puts in place seven wellbeing goals for Wales. These are for a more equal, prosperous, resilient, healthier and globally responsible Wales, with cohesive communities and a vibrant culture and thriving Welsh language. Under section (10)(1) of the Act, the Welsh Ministers must (a) publish indicators (“national indicators”) that must be applied for the purpose of measuring progress towards the achievement of the wellbeing goals, and (b) lay a copy of the national indicators before Senedd Cymru. Under section 10(8) of the Well-being of Future Generations Act, where the Welsh Ministers revise the national indicators, they must as soon as reasonably practicable (a) publish the indicators as revised and (b) lay a copy of them before the Senedd. These national indicators were laid before the Senedd in 2021. The indicators laid on 14 December 2021 replace the set laid on 16 March 2016.
Information on the indicators, along with narratives for each of the wellbeing goals and associated technical information is available in the Wellbeing of Wales report.
Further information on the Well-being of Future Generations (Wales) Act 2015.
The statistics included in this release could also provide supporting narrative to the national indicators and be used by public services boards in relation to their local wellbeing assessments and local wellbeing plans.
UK nations statistical publications
Ambulance response
- England Ambulance Quality Indicators (NHS England)
- Northern Ireland emergency care and ambulance statistics (Department of Health, Northern Ireland)
- Scottish Ambulance Service Unscheduled Care Operational Statistics (Scottish Ambulance Service)
Emergency departments
- Northern Ireland emergency care waiting times (Department of Health, Northern Ireland)
- England A&E attendances and emergency admissions (NHS England)
- Scotland accident and emergency statistics (Public Health Scotland)
Planned care waiting times
- England Referral to Treatment (RTT) Waiting Times (NHS England)
- England diagnostic waiting times and activity (NHS England)
- Scotland NHS waiting times stage of treatment statistics (Public Health Scotland)
- Scotland diagnostic waiting times (Public Health Scotland)
- Northern Ireland outpatient waiting times (Department of Health, Northern Ireland)
- Northern Ireland inpatient waiting times (Department of Health, Northern Ireland)
- Northern Ireland diagnostic waiting times (Department of Health, Northern Ireland)
Cancer waiting times
Next update
19 November 2026
We want your feedback
We welcome any feedback on any aspect of these statistics which can be provided by email to stats.healthinfo@gov.wales.
